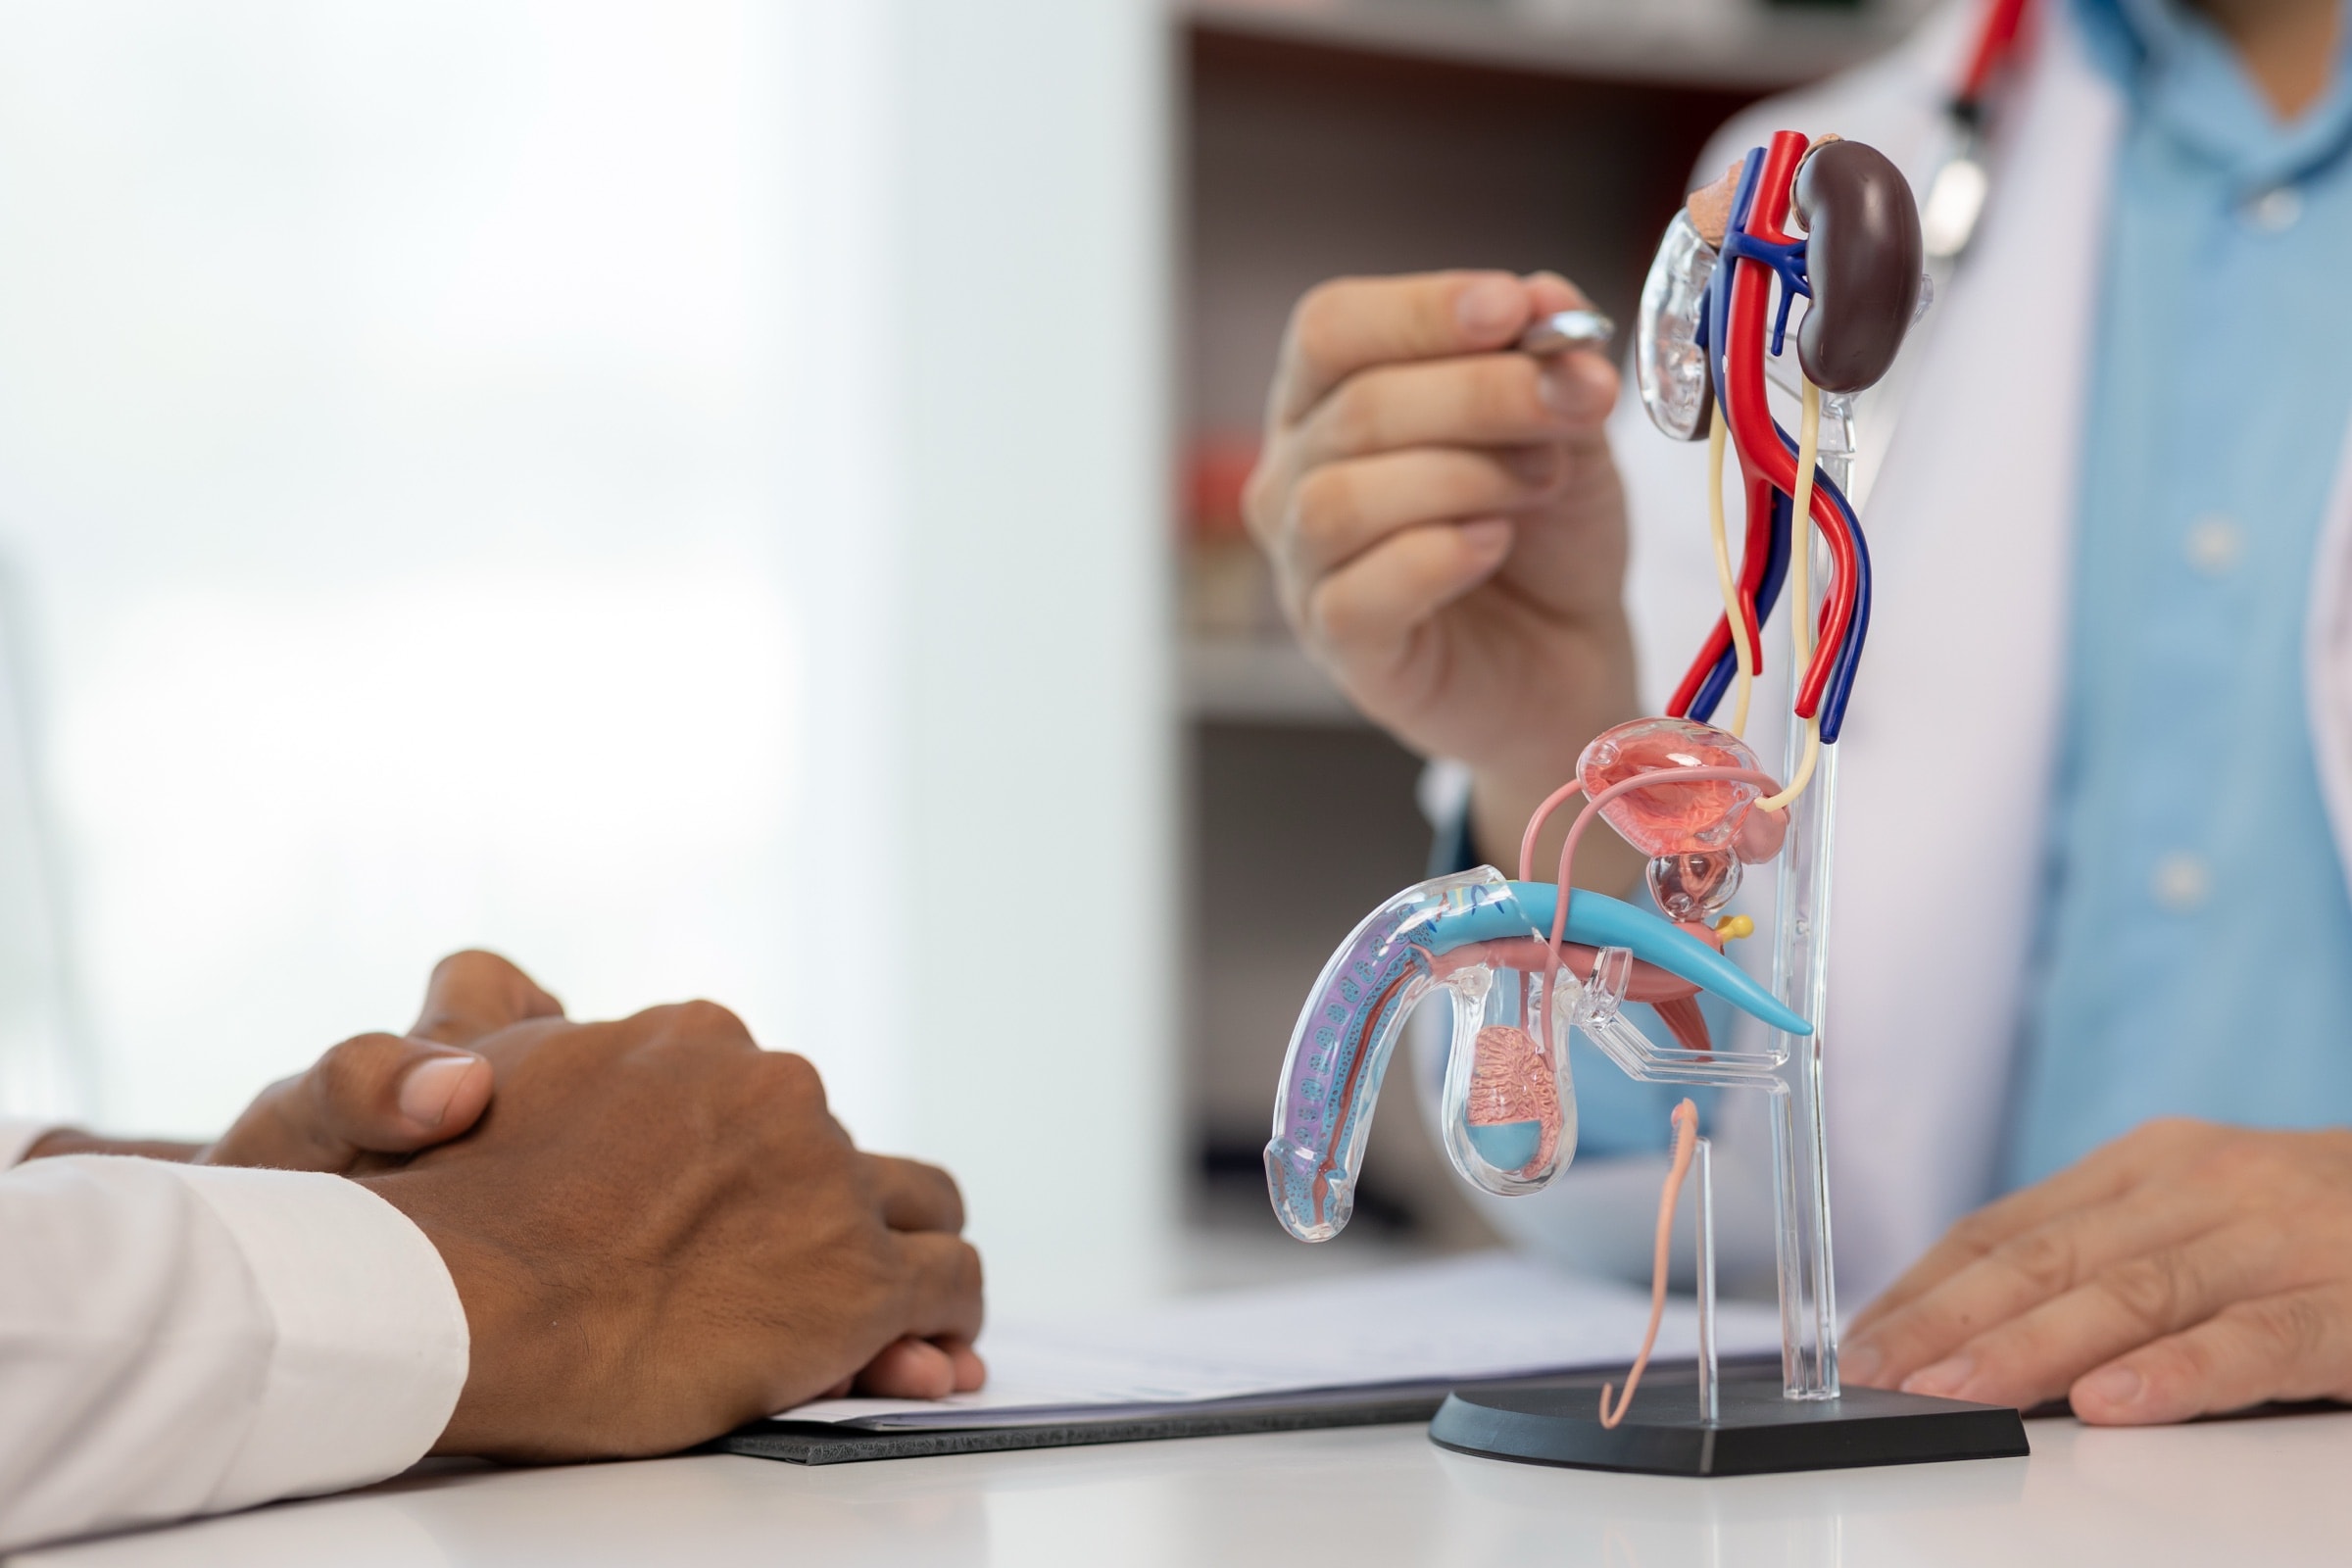
Prostatitis Without Infection: Why Antibiotics Often Fall Short
Most chronic prostatitis is not a bacterial infection. Under the classification urologists use, which comes from the National Institutes of Health, the most common type is chronic prostatitis/chronic pelvic pain syndrome, and in that type testing does not find an infection. That is why antibiotics often do not fix it. In many men, the pain and urinary symptoms come from the muscles and nerves around the prostate.
Learn moreHow Dr. Gordon treats chronic prostatitisA name that points the wrong way
"Prostatitis" sounds like an infected prostate. So when a man has pelvic pain, burning or urinary trouble, the usual first step is a course of antibiotics. Testing for infection is important and should always be done.
The trouble starts when the cultures come back negative, the antibiotics do not help, and another course follows anyway, with no one looking at the muscles.
The four types of prostatitis
This system has four categories:
- Acute bacterial prostatitis. A sudden infection of the prostate that needs prompt medical treatment.
- Chronic bacterial prostatitis. A chronic or recurring infection of the prostate, treated with a longer course of antibiotics.
- Chronic prostatitis/chronic pelvic pain syndrome (CP/CPPS). Pelvic pain and urinary symptoms with no infection found. This is the most common type.
- Asymptomatic inflammatory prostatitis. Inflammation of the prostate with no symptoms.
Only the first two are infections. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) calls CP/CPPS the most common and least understood form, and estimates it affects 10 to 15 percent of men in the United States, at any age. The exact cause is not known.
Why antibiotics often do not fix it
If bacteria are not driving the symptoms, an antibiotic has nothing to treat. The NIDDK says plainly that antibiotics will not help treat nonbacterial prostatitis, although a doctor may prescribe them at first to rule out a bacterial infection.
In a 2004 trial, 196 men with long-standing CP/CPPS took ciprofloxacin, tamsulosin, both, or a placebo for six weeks. Neither drug did significantly better than placebo.
If your tests are clear and you wonder how the pain can be real, I wrote about that in Why Pelvic Floor Pain Gets Missed, and What a Muscle Exam Can Find.
The muscle and nerve side
The prostate sits inside a sling of pelvic floor muscles, and it is surrounded by nerves that also supply the bladder, perineum, penis and rectum. When those muscles hold constant tension, they develop trigger points that refer pain to the tip of the penis, the testicles, the perineum and the area above the pubic bone. Tight muscles also squeeze the urethra, which helps explain a slow stream, urgency and the feeling of not emptying fully.
The pudendal nerve, which supplies the penis, perineum and rectum, can become sensitive from sitting, cycling and tight muscle around it, adding burning and tingling. After months of symptoms, the nervous system can also start to amplify normal bladder and pelvic signals, and that keeps the cycle running.
A 2015 urology consensus guideline notes that symptoms may come from abnormal pelvic muscle spasm and tenderness, and that therapies aimed at relaxing and coordinating the pelvic floor, along with myofascial trigger point release, may help improve symptoms. The NIDDK lists acupuncture among the other treatments men may try. Women can develop the same pattern, which I cover on the chronic pelvic pain syndrome page.
What changes once you know
Once infection has been ruled out, the next step is to find which muscles and nerves are keeping the symptoms going.
Your urologist still manages testing and medications. The first visit runs 60 to 75 minutes. I examine the pelvic floor from the outside, with no internal exam, and I do not perform prostate exams. Dry needling targets the pelvic floor muscles around the prostate and the deep hip and inner thigh muscles that refer pain into the groin. The needles go in through the skin of the buttock, perineum or inner thigh, never through the rectum. Alongside dry needling, I use neuro-functional acupuncture, built on neuroscience and evidence-based practice. Unlike regular electroacupuncture, the needles and gentle electrical stimulation are mapped to the specific nerves involved, such as the sacral and pudendal nerves. It works in three ways. It neurorehabilitates, helping irritated tissues and nerve receptors recover. It neuromodulates, shifting the body's own pain-relieving chemistry. It neuroregulates, calming the nerve signals and circuits that keep burning, urgency and pelvic pain going. Results vary from person to person.
See a doctor first if you have fever or chills with pelvic or urinary symptoms; inability to urinate; visible blood in the urine or semen; sudden, severe testicular pain or swelling; a new lump in the testicle; or new numbness in the saddle area or loss of bladder or bowel control. If you have any of these, contact your doctor or go to the nearest emergency department.
If you are not sure what is causing your pain, try the My Symptoms tool.
Questions people ask
What tests should I ask my urologist about?
Ask whether your urine has been cultured for bacteria, and whether a test comparing urine before and after a prostate massage makes sense for you. That is how urologists look for chronic bacterial prostatitis. If the results are clear, ask what else could be driving your symptoms.
Should I keep taking antibiotics if they have not helped?
Do not stop or start any medication without your urologist. The 2015 urology guideline advises a repeat course only when a bacterial cause is confirmed, so if cultures have not found bacteria, it is fair to ask whether another course makes sense.
Why does it flare after a long drive or a stressful week?
Long sitting presses on the pelvic floor and the pudendal nerve, and stress tends to tighten the pelvic floor further. When the muscles are already guarded, that can be enough to bring symptoms back. Tell your doctor about any symptom that is new or different.
References
- Rees J, et al. Diagnosis and treatment of chronic bacterial prostatitis and chronic prostatitis/chronic pelvic pain syndrome: a consensus guideline. BJU Int. 2015;116(4):509-525.
- Alexander RB, et al. Ciprofloxacin or tamsulosin in men with chronic prostatitis/chronic pelvic pain syndrome: a randomized, double-blind trial. Ann Intern Med. 2004;141(8):581-589.
- National Institute of Diabetes and Digestive and Kidney Diseases. Prostatitis: Inflammation of the Prostate. niddk.nih.gov. Last reviewed July 2014.