
Pelvic Floor Condition
Chronic Prostatitis
By Dr. Anthony J. Gordon, Doctor of Acupuncture | Last reviewed September 2026
You were told it was prostatitis. You took the antibiotics, maybe more than one course, and the burning, pressure and urgency came back anyway. Most chronic prostatitis is not a prostate infection. It is usually a pelvic floor and nerve problem that sits right next to the prostate and feels like it comes from it.
Prefer to talk it through? Call (516) 597-5400. Most new patients are seen within one to two weeks.
Overview
Understanding Chronic Prostatitis
Doctors divide prostatitis into categories. Acute and chronic bacterial prostatitis involve a real infection and need medical treatment. By far the most common type, however, is chronic nonbacterial prostatitis, also called chronic prostatitis / chronic pelvic pain syndrome. In this type, repeated testing does not find an infection, yet symptoms continue for months or years.
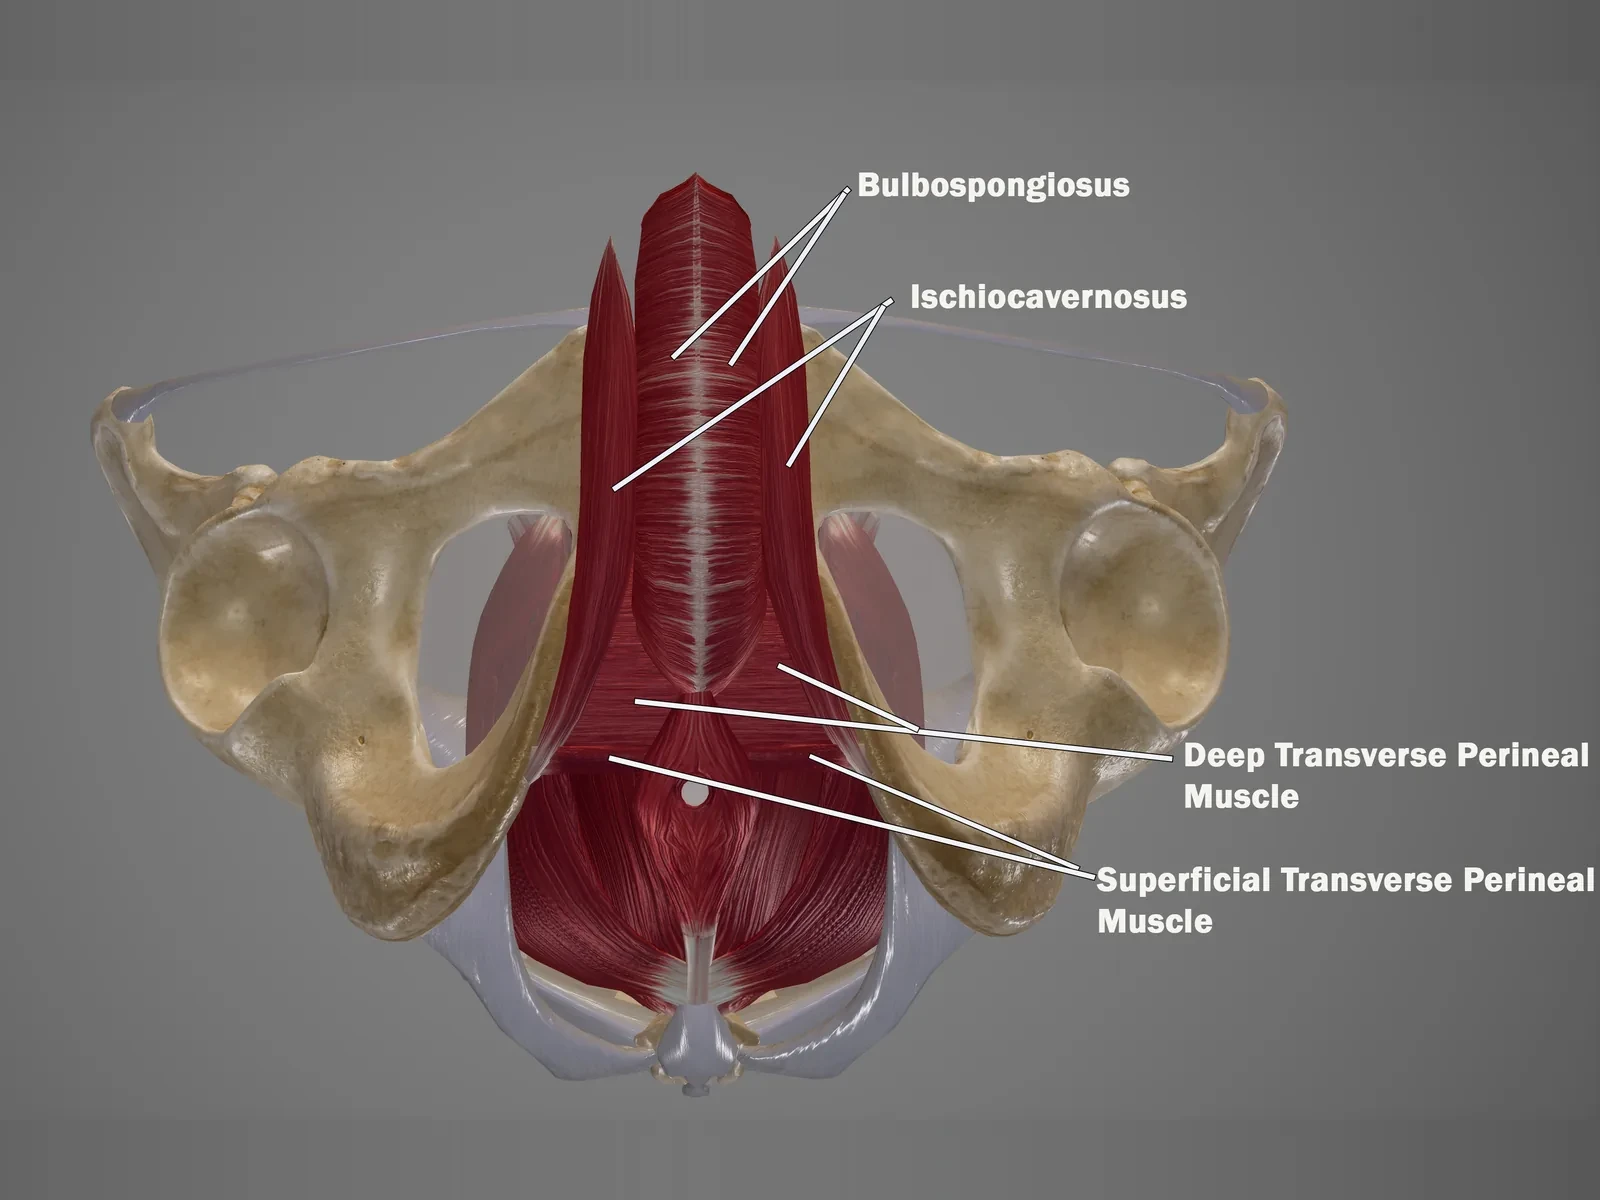
The prostate sits inside a sling of pelvic floor muscles and is surrounded by nerves that also supply the bladder, perineum, penis and rectum. When those muscles hold constant tension, they develop trigger points that refer pain to the tip of the penis, the testicles, the perineum and above the pubic bone. They also squeeze the urethra, which explains slow flow, urgency and the feeling of not emptying fully. Stress, long hours of sitting, cycling and heavy lifting all feed the pattern.
Your urologist manages infection testing, medications and anything that needs medical care. Dr. Gordon's focus is the pelvic floor, the surrounding hip muscles and the irritated nerves that keep symptoms going after the medical side has been addressed.
Chronic Prostatitis at a Glance
Also called
Chronic nonbacterial prostatitis, CP/CPPS, prostatodynia
Who it affects
Men of all ages, most often between 20 and 50, frequently active or under long-term stress
Typical workup results
Negative urine and semen cultures, normal or mildly abnormal prostate exam, limited lasting benefit from antibiotics
Where it is felt
Perineum, tip of the penis, testicles, above the pubic bone, rectum and low back
Main drivers
Pelvic floor tension and trigger points, pudendal nerve irritation, sitting and training load, stress
The Gap in Care
What Tests Check, and What They Can Miss
Testing for infection is important and should always be done. When cultures keep coming back clean, though, repeating antibiotics rarely changes the outcome because the source was never bacterial.
What routine testing is looking for
- Bacteria in urine, semen or prostate fluid
- Enlarged prostate or nodules on exam
- Bladder or urethral problems on scope
- Stones or structural changes on imaging
What often keeps symptoms going
- Pelvic floor muscles that squeeze around the prostate and urethra
- Trigger points that refer pain to the penis, testicles and perineum
- An irritated pudendal nerve from sitting or cycling
- Tight inner thigh and deep hip muscles
- A stress response that keeps the pelvic floor clenched
These are found by examining the muscles and nerves around the prostate, not the prostate itself. That is where Dr. Gordon's evaluation focuses.
Signs & Symptoms
Does This Sound Like You?
Symptoms vary from person to person. These are the patterns Dr. Gordon sees most often.
Perineal or rectal pressure
A deep ache or the feeling of sitting on a ball, worse after long periods of sitting, driving or cycling.
Pain at the tip of the penis or in the testicles
Referred pain that can shift sides and often has no local cause when examined.
Urinary urgency, frequency or slow flow
Going often, a hesitant or weak stream, dribbling, or feeling like the bladder never fully empties.
Burning with urination
Stinging or burning during or after urination even when urine tests are clean.
Pain with or after ejaculation
Discomfort during orgasm or an ache in the pelvis, penis or testicles that lingers for hours afterward.
Pain above the pubic bone or in the low back
An ache in the lower abdomen, groin or sacrum that rises and falls with other symptoms.
Root Causes
The Four Drivers Dr. Gordon Looks For
Most people have more than one of these in play. Finding which one leads makes treatment more efficient.
Pelvic floor tension around the prostate
The levator ani and deeper pelvic muscles surround the prostate and urethra. Constant tension compresses these structures and creates trigger points that refer pain throughout the pelvis.
Pudendal nerve irritation
The pudendal nerve supplies the penis, perineum and rectum. Pressure from sitting, cycling and tight surrounding muscle can make it sensitive, adding burning and tingling.
Hip and inner thigh muscles
Tight adductors, obturator internus and deep rotators tug on the pelvic floor and are common sources of groin and testicular referral.
Stress and nervous system sensitization
Stress tightens the pelvic floor in many men. After months of symptoms, the nervous system amplifies normal bladder and pelvic signals, which keeps the cycle running.
Your First Visit
How Dr. Gordon Evaluates Chronic Prostatitis
The initial evaluation runs 60 to 75 minutes. You leave with a clear picture of what is driving your symptoms, a written plan, a realistic timeline, and in most cases your first treatment.
Records and history review
Dr. Gordon reviews your urologist's findings, imaging, medications and past treatments so he knows what has been ruled out and what has already been tried.
External muscle and nerve mapping
Hands-on assessment of the abdomen, groin, inner thighs, hips and buttocks to find trigger points and nerve sensitivity that reproduce your pain.
External pelvic floor assessment
The pelvic floor muscles are examined from the outside, with no internal exam. With you draped for comfort, gentle pressure around the perineum, sit bones, tailbone and inner thighs checks tone, tenderness and trigger points.
Sitting, training and stress screen
Dr. Gordon looks at how many hours you sit, whether you cycle or lift, your breathing and bracing habits, and how stress affects your symptoms.
Plan and coordination
A clear plan, plus communication with your urologist or pelvic floor PT when that helps your care.
When to see a physician first
- Fever or chills with pelvic or urinary symptoms
- Inability to urinate
- Visible blood in the urine or semen
- Sudden, severe testicular pain or swelling
- A new lump in the testicle
- New numbness in the saddle area or loss of bladder or bowel control
If you have any of these, contact your doctor or go to the nearest emergency department.
Bring to your first visit
Records
Recent lab results, imaging reports and specialist notes. These can also be faxed ahead.
Treatment history
A short list of what you have tried and what did or did not help.
Clothing
Something comfortable and loose fitting.
Treatment
How Dr. Gordon Treats It
These are the tools Dr. Gordon uses most often for chronic prostatitis, chosen from your exam findings.
Primary approach
Intrapelvic & Extrapelvic Dry Needling
Dr. Gordon holds ASE certification in both intrapelvic and extrapelvic dry needling. Treatment targets the pelvic floor muscles around the prostate, along with the adductors and deep hip muscles that refer pain into the groin and testicles. The needles go in through the skin of the buttock, perineum or inner thigh, never through the vagina or rectum.
Learn about pelvic floor treatmentNerve focus
Neuro-Functional Acupuncture
Gentle electro-acupuncture along the sacral and pudendal nerve pathways to calm burning, urgency and nerve sensitivity.
See servicesBetween visits
Daily Habits & Team Coordination
Guidance on sitting, cycling, training, bladder habits and stress, plus coordination with your urologist so you are not stuck on repeat antibiotic courses without a plan.
Referring provider? Contact the clinicWhat to Expect
A Typical Recovery Arc
Visits 1 to 3
Find the source
Dr. Gordon confirms which muscles and nerves are driving symptoms. Many men notice less perineal pressure or easier urination early on.
Visits 4 to 8
Settle the pattern
Pain, urgency and post-ejaculation flares become less frequent and less intense. Sitting and training become easier.
Visits 9 to 12 and beyond
Build resilience
Visits are spaced out as improvement holds, with a plan for stress, sitting and early flare control.
Most patients are seen weekly or every other week during active care. Individual results vary with how long symptoms have been present and how reactive they are. Progress is reassessed at every visit.
Not sure how to describe it? Put your pain or discomfort into words before your visit
"Dr. Gordon is thoughtful, thorough and incredibly knowledgeable. He has significantly helped me with pain management and pelvic floor issues. I am grateful to have his expertise in my corner."
Dina Isola, Google Review
Chronic Prostatitis Questions
Answers About Chronic Prostatitis
Still unsure whether this is the right fit? Reach out before you book and Dr. Gordon will talk through your history with you.
Some antibiotics used for prostatitis also have anti-inflammatory effects, and symptoms naturally rise and fall over weeks. Temporary improvement is common even when bacteria were never the cause. If symptoms return each time, it is worth looking at the pelvic floor.
In most men, yes. The medical term is chronic prostatitis / chronic pelvic pain syndrome. It describes pelvic pain and urinary symptoms without a confirmed infection.
No. Prostate exams and medical testing are done by your urologist. Dr. Gordon's assessment and treatment focus on the pelvic floor muscles and nerves. The pelvic floor is examined externally, with no internal exam.
Often yes, with adjustments. Dr. Gordon looks at your saddle, riding position, lifting technique and breathing, and helps you change what is loading the pelvic floor rather than stopping everything.
Long-standing chronic prostatitis usually needs eight to twelve sessions with reassessment along the way, typically weekly at first and then spaced out. Dr. Gordon gives you an estimate at your first visit.
Chronic nonbacterial prostatitis is not known to cause prostate cancer. Questions about fertility, PSA levels or cancer screening should go to your urologist, who can advise you based on your history.
Before You Book
General Questions
The clinic is an out-of-network practice. The initial evaluation is $300 and follow-up visits are $250. After each visit you receive a detailed superbill to submit to your PPO plan for possible reimbursement. FSA and HSA cards are accepted, and the clinic can run a complimentary benefits check before your first appointment. The check is a courtesy, so please confirm your coverage with your plan. See Insurance & Fees for details.
The first evaluation is 60 to 75 minutes and usually includes treatment. Follow-up visits run 45 to 60 minutes.
Yes. Call (516) 597-5400 or send a message through the contact page. This is especially helpful if your case is complex and you want to understand the approach before committing to a full evaluation.
1508 Union Turnpike, Suite 133, North New Hyde Park, NY 11040, with free parking on site. The clinic is an easy drive from Manhasset, Great Neck, Garden City, Lake Success, Floral Park and Mineola. Early morning, evening and weekend hours are available.
Most people feel a quick muscle twitch or a deep ache that lasts a few seconds. That twitch is a normal sign the trigger point is releasing. Mild soreness for 24 to 48 hours afterward, similar to a hard workout, is common. Depth, angle and stimulation are adjusted to your comfort.
Both use the same fine, sterile, single-use needles. Dry needling targets specific trigger points and tight bands in muscle based on your exam. Neuro-functional acupuncture targets nerve pathways, often with gentle electrical stimulation, to calm nerve sensitivity. For chronic prostatitis, Dr. Gordon commonly uses both.
When performed by a trained, licensed provider with detailed knowledge of anatomy, it has a strong safety record. Tell Dr. Gordon if you take blood thinners, have a bleeding disorder, are pregnant or have a weakened immune system so he can plan accordingly.
It is a technique that reaches the deep pelvic floor muscles, including the levator ani, obturator internus and coccygeus, to release trigger points and restore normal muscle function. The needles go in through the skin of the buttock, perineum or inner thigh, never through the vagina or rectum. Dr. Gordon holds ASE certification in this technique, which few practitioners in New York have.
Yes. Your privacy and comfort come first. When undressing is needed for the area being treated, you are fully draped. Needles are placed through the skin only, and nothing is ever inserted into the vagina or rectum. You can pause or stop at any time.
Yes. Many men put off care for pelvic and genital symptoms because the topic feels awkward. Dr. Gordon keeps things straightforward and clinical, explains every step, and treats adults of all genders and identities in a respectful, welcoming setting.
It helps to have had a medical workup so serious causes have been checked. If you have not seen a urologist for these symptoms yet, call the clinic to talk through the best order of steps.

About Dr. Anthony J. Gordon
Dr. Anthony J. Gordon is a Doctor of Acupuncture licensed in New York and board certified. He holds ASE certification in intrapelvic and extrapelvic dry needling, along with advanced certifications in Functional Dry Needling and Neuro-Functional Acupuncture. With more than 18 years of clinical experience and over 3,000 complex cases treated, he focuses on pelvic, spinal and orthopedic conditions that have not responded to standard care, and works closely with each patient's physicians and physical therapists.
Read Dr. Gordon's full bioFurther Reading
Why Pelvic Floor Pain Gets Missed, and What a Muscle Exam Can Find
From the blog: why routine tests miss tight pelvic floor muscles, and what a gentle external exam can find.
Prostatitis Without Infection: Why Antibiotics Often Fall Short
From the blog: Most chronic prostatitis is not a bacterial infection. Why antibiotics often fall short, and the pelvic muscles and nerves that keep symptoms going.
Pain at the Tip of the Penis: A Pelvic Floor Cause
From the blog: Pain at the tip of the penis with clear tests can be referred from tight pelvic floor muscles. Why it happens, what to rule out first, and what helps.
Book an Evaluation for Chronic Prostatitis
Book a full evaluation with Dr. Gordon and find out which pelvic floor muscles and nerves are behind your symptoms.
Early morning, evening and weekend appointments available. Free on-site parking.
Symptoms
Common Symptoms of Chronic Prostatitis
Keep Reading